
GIE Associate Editor Monique Barakat, MD, highlights this article from the October issue: “Endoscopic ultrasound–guided radiofrequency ablation for intraductal papillary mucinous neoplasms with worrisome features: long-term outcomes in nonsurgical patients (with video)” by Julien Barras, MD, et al.

Earlier EUS-guided ablation series largely excluded pancreatic cysts with worrisome features, which is precisely why they could not speak to the patients who trouble us most: the frail, comorbid patients with a branch-duct intraductal papillary mucinous neoplasm (IPMN) and a mural nodule for whom pancreatectomy—roughly 20% to 40% morbidity, about 5% perioperative mortality, and low-grade dysplasia in more than one-half of resected specimens—is not a realistic option.
This study inverts that selection: 98% of treated lesions carried at least 1 worrisome feature, 38% had a mural nodule ≥5 mm, and every patient was either unfit for surgery or declined it. To our knowledge, it is the largest EUS-guided radiofrequency ablation (RFA) experience with IPMNs reported to date (50 patients, 58 lesions, 62 procedures) and, unusually, the follow-up is long enough to matter: a mean of 4.1 years after ablation. Technical success was 100%, local control was achieved in 98% of lesions, no cancer arose from any ablated lesion, and adverse events, although the 27% rate initially appears high, were overwhelmingly self-limited abdominal pain.
This article fills a specific and clinically pressing evidence gap with data granular enough to use at the bedside: the 27% adverse event figure resolves into 21% mild adverse events in GI endoscopy I pain, 3 cases of pancreatitis (1 necrotizing), 1 biliary injury, and no procedure-related deaths. The authors identify predictors of adverse events (younger age, prior IPMN-related pancreatitis, smaller main pancreatic duct, and repeat sessions) that inform a consent conversation.
There are practical technical lessons, too, notably that no lesion in the uncinate process or isthmus achieved a complete radiologic response. Finally, the authors’ restraint is impressive: they are explicit that local control is a clinical and radiologic surrogate rather than proof-of-histologic eradication, that cyst shrinkage may reflect necrosis or mucin loss rather than cure, that 8% of patients developed cancer elsewhere in the gland, and that none of this should be extrapolated to surgically fit patients.
The take-home points are:
- In nonsurgical patients, EUS-guided RFA achieved local control in 98% of branch-duct IPMNs with worrisome features over a mean of 4.1 years, with no cancer arising from a treated lesion.
- Technical success was 100%, and adverse events (27% of procedures) were mostly mild pain, with 3 pancreatitis cases, 1 biliary injury, and no procedure-related deaths.
- Resolution of worrisome features, not cyst eradication, is the meaningful end point—only 17% disappeared radiologically, whereas 86% shrank.
- Smaller cysts and fewer worrisome features predicted better response, and uncinate or isthmic lesions achieved no complete responses.
- RFA treats a cyst, not a pancreas: 8% of patients developed cancer distant from the ablated lesion, so lifelong whole-gland surveillance remains mandatory.
- This is not an alternative to resection in surgically fit patients, and prospective multicenter data are needed to refine selection criteria.
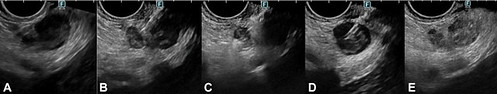
Chronological steps of EUS-guided radiofrequency ablation of an intraductal papillary mucinous neoplasm (IPMN). A, IPMN before radiofrequency ablation. B, Radiofrequency ablation of the mural nodule. C, Appearance of the mural nodule at the end of ablation. D, Radiofrequency ablation of the IPMN. E, Final appearance of the IPMN at the end of ablation.
Read the full article online.
The information presented in Endoscopedia reflects the opinions of the authors and does not represent the position of the American Society for Gastrointestinal Endoscopy (ASGE). ASGE expressly disclaims any warranties or guarantees, expressed or implied, and is not liable for damages of any kind in connection with the material, information, or procedures set forth.

